Pediatric Diaphragmatic Plication Surgery is a surgical procedure performed to tighten and flatten an abnormally elevated or weak diaphragm so that it can move more effectively during breathing. The diaphragm is the main muscle responsible for breathing. When one side becomes weak or paralyzed, it may move abnormally and rise into the chest, limiting lung expansion.
During diaphragmatic plication, the surgeon folds and sutures the affected portion of the diaphragm to make it tighter and reduce its excessive elevation. This helps create more space for the lung to expand and can improve breathing mechanics.
The procedure may be performed through open surgery or a minimally invasive approach, depending on the child’s age, condition, previous surgeries, and the surgeon’s assessment. It may be considered for children with diaphragmatic paralysis or eventration who have significant breathing difficulties or other related symptoms.
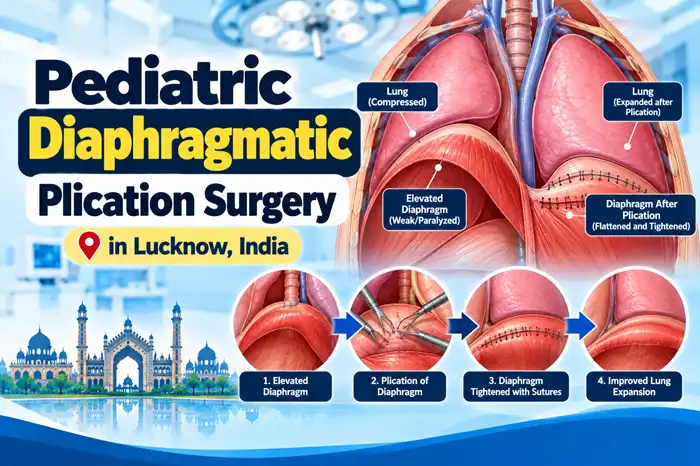
A child may be considered for diaphragmatic plication when abnormal diaphragm movement or elevation significantly affects breathing or lung expansion.
Surgery may be considered when a child has:
The decision depends on the severity of symptoms, imaging findings, the child’s respiratory status, and whether recovery of diaphragm function is expected without surgery.
The main purpose of diaphragmatic plication is to improve the position and mechanical function of the affected diaphragm.
The procedure may help to:
The outcome depends on the underlying cause, the child’s lung condition, and the severity of diaphragm dysfunction.
The procedure is performed under general anesthesia.
The surgeon accesses the affected diaphragm through an incision or minimally invasive surgical ports. The elevated or weakened portion is folded and secured with sutures to make the diaphragm flatter and tighter.
The general steps include:
The goal is to improve the diaphragm’s position without unnecessarily restricting the movement of the chest or causing injury to nearby structures.
Open diaphragmatic plication involves making an incision in the chest or, in selected cases, the abdomen to access the diaphragm.
The surgeon places sutures in the diaphragm to fold and tighten the elevated section. The exact incision depends on the child’s anatomy, the location of the abnormality, and the planned surgical approach.
Open surgery may be appropriate for children with complex anatomy, previous operations, or situations in which direct access is considered preferable.
Thoracoscopic diaphragmatic plication is a minimally invasive technique performed through small incisions in the chest.
A camera and specialized instruments allow the surgeon to visualize the diaphragm and place sutures to reduce its elevation.
Potential advantages in selected children include:
Thoracoscopic surgery is not suitable for every child. The decision depends on the child’s size, clinical stability, anatomy, and the surgeon’s experience with the technique.
In selected cases, diaphragmatic plication may be performed using a laparoscopic approach through small incisions in the abdomen.
The surgeon accesses the diaphragm from below and places sutures to tighten the affected area.
The laparoscopic approach may be considered when the abdominal route provides suitable access. The choice between thoracoscopic, laparoscopic, and open surgery depends on the location of the problem and the child’s individual circumstances.
Diaphragmatic plication may be considered when the diaphragm is paralyzed or significantly weakened and does not move normally during breathing.
In such cases, the diaphragm may rise during inspiration rather than assisting lung expansion. Plication reduces excessive elevation and provides a more stable position for the affected side.
Some children may recover diaphragm function over time, so the surgical team considers the cause, duration, severity, and likelihood of spontaneous recovery before recommending surgery.
Diaphragmatic eventration is a condition in which part or all of the diaphragm is abnormally elevated because of thinning or weakness while remaining continuous.
When eventration causes significant respiratory symptoms, plication may be used to flatten and tighten the affected area.
The surgeon determines whether surgery is necessary based on symptoms, imaging, lung expansion, and the child’s overall condition.
The timing depends on the child’s symptoms and the underlying cause.
Some children can be observed because diaphragm function may improve over time. Others may need earlier intervention if breathing is significantly affected.
Diaphragmatic plication is an established surgical option for selected children with clinically significant diaphragm dysfunction. However, as with any operation, it carries risks.
The surgical team evaluates the child’s respiratory condition, underlying disease, anesthesia requirements, and expected benefits before recommending the procedure.
Children with significant lung disease or other complex medical conditions may require closer monitoring before and after surgery.
Potential benefits include:
The degree of improvement varies, and plication does not guarantee normal diaphragm movement or complete resolution of respiratory symptoms.
Possible complications include:
The risk depends on the child’s age, medical condition, surgical approach, and complexity of the procedure.
Recovery depends on the child’s condition before surgery and the approach used.
After surgery, the medical team monitors breathing, oxygen levels, pain, and signs of complications. Some children may require respiratory support for a period, particularly if they were dependent on ventilation before the operation.
Recovery may include:
Children who were critically ill before surgery may need a longer recovery period.
Parents should follow the surgeon’s instructions regarding wound care, medicines, activity, and follow-up.
Important measures include:
Seek urgent medical care if the child develops severe breathing difficulty, bluish lips, or a sudden deterioration in condition.
Follow-up helps the surgical team assess healing and respiratory improvement.
The team may review:
Further treatment depends on the child’s response to surgery and any underlying lung or neurological condition.
The timing depends on the child’s age, surgical approach, and recovery.
Light activities can generally be resumed gradually according to medical advice. Strenuous activity should be avoided until the surgical team confirms that recovery is satisfactory.
Children with ongoing respiratory or neurological conditions may need an individualized rehabilitation and activity plan.
Many appropriately selected children experience improvement in breathing mechanics after plication. However, long-term outcomes depend on the cause of diaphragm dysfunction and the child’s overall respiratory health.
Some children may continue to require respiratory support or treatment for underlying lung disease. Follow-up helps assess breathing, growth, activity tolerance, and whether further intervention is needed.
The cost varies according to the surgical approach, the child’s medical condition, and the hospital’s facilities.
Factors that may affect the total cost include:
Parents should discuss the expected treatment plan and obtain an individualized estimate from the hospital.
Before deciding on diaphragmatic plication, parents should understand the cause of the diaphragm problem, the likelihood of spontaneous recovery, and the expected benefits and risks of surgery.
Useful questions to discuss with the pediatric surgeon include:
It is a surgical procedure that tightens and flattens an elevated or weak diaphragm to improve lung expansion and breathing mechanics.
A child may need surgery when diaphragm paralysis or eventration causes significant breathing difficulty, poor lung expansion, or difficulty coming off ventilatory support.
Yes. Open surgery is one option. Thoracoscopic or laparoscopic techniques may also be considered for selected children.
Some children may experience improvement in diaphragm function over time. The likelihood depends on the cause and severity, so the surgical team assesses whether observation or surgery is more appropriate.
Recovery varies with the child’s health, severity of diaphragm dysfunction, and surgical approach. Children who need respiratory support before surgery may require longer monitoring.
Plication can improve diaphragm position and breathing mechanics, but it does not guarantee complete or permanent resolution of symptoms. Outcomes depend on the underlying cause and the child’s respiratory health.
No. The minimally invasive approach depends on the child’s age, size, anatomy, clinical stability, and the surgeon’s assessment.
Dr. Muni Varma offers advanced Pediatric Diaphragmatic Plication Surgery for Children in Lucknow, India. With more than 10 years of experience, he uses a careful and child-focused approach to provide appropriate evaluation, surgical planning, and follow-up care. He helps parents understand the treatment options, expected recovery, and care required for children with diaphragm dysfunction.
