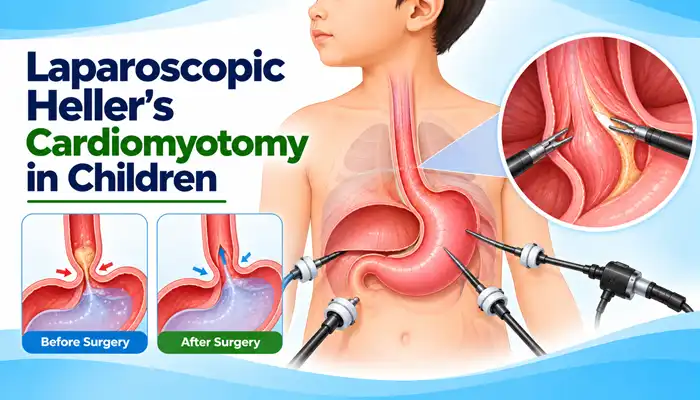
Laparoscopic Heller’s cardiomyotomy is a minimally invasive surgical procedure used to treat achalasia in children. During the operation, the surgeon makes small incisions in the abdomen and uses a camera and specialised instruments to divide the tight muscle fibres at the lower end of the esophagus, where it joins the stomach.
The lower esophageal sphincter is a muscular valve that normally relaxes when food passes from the esophagus into the stomach. In achalasia, this valve does not relax properly, and the normal coordinated movement of the esophagus is impaired. As a result, food and liquids may remain in the esophagus instead of passing easily into the stomach.
Laparoscopic Heller’s cardiomyotomy in children aims to reduce the resistance at the lower esophageal sphincter and improve swallowing. A partial fundoplication, which involves wrapping part of the upper stomach around the lower esophagus, may also be performed to help reduce gastroesophageal reflux after surgery.
The procedure may be recommended for children with confirmed achalasia who have significant swallowing difficulties, regurgitation, nutritional problems, or persistent symptoms despite other treatments. The treatment plan depends on the child’s age, symptoms, diagnostic findings, and overall health.
A pediatric surgeon may recommend laparoscopic Heller’s cardiomyotomy when achalasia significantly affects a child’s ability to swallow, eat, drink, or maintain healthy growth.
The procedure may be considered in children with:
Not every child with achalasia requires surgery immediately. Treatment options may include pneumatic dilation, botulinum toxin injection in selected cases, or peroral endoscopic myotomy (POEM). The specialist discusses the benefits and limitations of these options before recommending an appropriate approach.
The primary purpose of laparoscopic Heller’s cardiomyotomy is to reduce the muscular resistance at the lower end of the esophagus so that food and liquids can pass more easily into the stomach.
The procedure aims to:
The procedure does not restore normal esophageal muscle contractions. Instead, it reduces the resistance at the lower esophageal sphincter to facilitate passage of food into the stomach. The degree of improvement varies, and some children may require additional treatment if symptoms persist or return.
Laparoscopic Heller’s cardiomyotomy is performed in an operating theatre under general anaesthesia. The exact technique depends on the child’s anatomy, the severity of achalasia, and the surgeon’s assessment.
The doctor reviews the child’s swallowing difficulties, regurgitation, nutritional status, previous treatments, and diagnostic results. The team assesses the esophagus and lower esophageal sphincter to confirm that the procedure is appropriate.
The child receives general anaesthesia and remains asleep throughout the operation. The anaesthesia team monitors breathing, oxygen levels, circulation, and other vital parameters.
The surgeon makes several small incisions in the abdomen. A laparoscope, which is a thin instrument with a camera, is inserted through one incision, and specialised surgical instruments are introduced through the others.
The camera provides a magnified view of the esophagus, the junction between the esophagus and stomach, and the surrounding structures.
The surgeon carefully identifies the lower esophageal sphincter and the lower portion of the esophagus. The operative area is prepared so that the tight muscle fibres can be divided while protecting the inner lining of the esophagus.
The surgeon makes a controlled longitudinal incision through the muscle fibres of the lower esophagus, extending across the esophagogastric junction and onto the upper part of the stomach.
This muscle division reduces the pressure that prevents food from passing easily into the stomach. The inner lining of the esophagus is preserved, and the surgeon checks carefully for any injury.
The surgeon assesses the extent of muscle division and checks for complications such as injury to the esophageal lining. The aim is to achieve adequate relaxation of the lower esophageal sphincter without causing unnecessary tissue damage.
A partial fundoplication may be performed during the same operation to help reduce acid reflux after the lower esophageal sphincter has been loosened.
Common approaches include Dor fundoplication, which uses the front portion of the stomach, and Toupet fundoplication, which uses a partial posterior wrap. The decision and technique depend on the child’s clinical circumstances and the surgeon’s assessment.
The surgeon checks the operative area, removes the instruments, and closes the small incisions. The child is transferred to the recovery area for monitoring and postoperative care.
The surgical approach depends on the child’s condition and the treatment plan.
This minimally invasive procedure uses small abdominal incisions, a camera, and specialised instruments to divide the muscle fibres at the lower esophagus. It is an established surgical treatment for symptomatic achalasia in children.
In selected cases, the operation may be performed through a larger incision in the abdomen or chest. Open surgery may be considered when minimally invasive surgery is unsuitable or when specific surgical circumstances require a different approach.
Dor fundoplication is a partial wrap using the front portion of the stomach. It may be performed alongside the myotomy to help reduce postoperative reflux.
Toupet fundoplication is a partial wrap around the back of the lower esophagus. It is another option that may be considered to help reduce reflux while avoiding a complete wrap that could create excessive resistance to swallowing.
POEM is an endoscopic procedure in which the surgeon reaches the esophageal muscle through the mouth and creates a tunnel within the esophageal wall to divide the tight muscle fibres. It does not require abdominal incisions.
Pneumatic dilation is another treatment option in selected children. The most appropriate approach depends on the child’s age, symptoms, esophageal anatomy, previous treatment, and the expertise available. Evidence comparing pediatric treatment approaches continues to evolve.
Preoperative investigations help confirm achalasia, assess the esophagus, and determine whether surgery is appropriate.
These may include:
Not every child requires every investigation. The specialist selects tests according to the child’s symptoms, age, previous results, and clinical condition.
For children with symptomatic achalasia who are suitable candidates, laparoscopic Heller’s cardiomyotomy may offer several benefits.
Potential benefits include:
The degree of benefit depends on the child’s condition and the severity of achalasia. Some children experience recurrent symptoms and may require further treatment.
Laparoscopic Heller’s cardiomyotomy is an established treatment for pediatric achalasia. However, like all surgical procedures, it carries risks.
Possible complications include:
The risk depends on the child’s condition, the surgical technique, and the experience of the treating team. Parents should discuss the expected benefits, limitations, alternatives, and possible complications before consenting to surgery.
Recovery depends on the child’s age, nutritional status, the complexity of the operation, and whether any complications occur.
The child is monitored while recovering from anaesthesia. The team checks pain, breathing, vital signs, and the child’s overall condition.
The timing of drinking and eating depends on the surgeon’s protocol and the child’s recovery. Some teams use a contrast study or other assessment when clinically indicated before advancing the diet, particularly if there is concern about an esophageal injury.
The child may initially receive clear liquids before progressing to other liquids and soft foods, followed by a more regular diet according to the treating team’s instructions.
Parents should follow the recommended food consistency, meal size, and pace of progression. The exact schedule varies between hospitals and individual patients.
The length of hospitalisation depends on pain control, oral intake, the child’s general condition, and whether further observation or testing is required. Children with complications may need a longer stay.
Before discharge, parents receive instructions about medicines, diet, wound care, activity, and follow-up. They should know whom to contact if swallowing difficulties, vomiting, fever, or chest or abdominal pain develop.
Appropriate aftercare helps support recovery and identify complications early.
Seek medical advice if the child develops worsening swallowing difficulties, repeated vomiting, persistent chest or abdominal pain, fever, or signs of dehydration. Inability to swallow liquids, severe pain, breathing difficulty, or sudden deterioration requires urgent medical assessment.
Follow-up is important to assess symptom improvement, nutritional recovery, and the possibility of reflux or recurrent swallowing difficulties.
The treating team may monitor:
Some children may need further evaluation or treatment, such as endoscopic dilation or repeat myotomy, if symptoms persist or recur. Follow-up should be tailored to the child’s progress rather than relying on symptoms alone.
The cost of laparoscopic Heller’s cardiomyotomy in children varies according to the hospital, the child’s age and condition, the complexity of the operation, and the length of hospitalisation.
Factors that may affect the overall cost include:
Parents should request an individual estimate after clinical evaluation so the expected expenses and included services can be explained clearly.
Before proceeding with laparoscopic Heller’s cardiomyotomy, parents should understand the diagnosis, the purpose of the operation, and the available alternatives.
Important points to discuss include:
Parents should inform the medical team about their child’s medicines, allergies, previous procedures, nutritional concerns, and any history of respiratory problems or aspiration.
It is a minimally invasive surgical procedure used to treat achalasia. The surgeon divides the tight muscle fibres at the lower end of the esophagus to reduce resistance and help food and liquids pass into the stomach.
The procedure may be recommended when achalasia causes significant swallowing difficulties, regurgitation, weight loss, poor growth, or persistent symptoms despite other treatments.
Published pediatric studies suggest that the procedure improves symptoms in many children. However, symptoms may persist or recur, and some children require additional treatment. Outcomes depend on the child’s condition and the surgical approach.
No. A partial fundoplication may be added to help reduce reflux, but the decision and the type of wrap vary. Evidence in children has not established one approach as best for every patient.
Heller’s cardiomyotomy is usually performed laparoscopically through small abdominal incisions. POEM is performed endoscopically through the mouth without abdominal incisions. Both aim to reduce resistance at the lower esophageal sphincter, but they differ in technique and potential risks.
Many children experience improved swallowing and can gradually return to a more regular diet. The speed of recovery varies, and dietary instructions should be followed carefully.
Yes. Some children experience recurrent swallowing difficulties after surgery. Further assessment may identify the cause and help determine whether additional treatment is needed.
Possible risks include esophageal injury, bleeding, infection, postoperative reflux, persistent swallowing difficulties, and the need for further treatment. The treating team explains the risks relevant to the individual child.
Recovery varies according to the child’s condition and the complexity of surgery. Oral intake is advanced gradually, and the return to routine activities depends on the child’s progress and the surgeon’s instructions.
Parents should seek medical advice for worsening swallowing difficulties, repeated vomiting, fever, persistent chest or abdominal pain, or signs of dehydration. Inability to swallow liquids, severe pain, or breathing difficulty requires urgent assessment.
Dr. Muni Varma offers Laparoscopic Heller’s Cardiomyotomy in Children in Lucknow, India. With more than 10 years of experience, he uses a careful and child-focused approach to provide appropriate evaluation, surgical planning, and follow-up care. He helps parents understand the surgical approach, available treatment options, and expected recovery for children requiring Heller’s cardiomyotomy.
