Pediatric Thoracotomy is a surgical procedure in which an incision is made in the chest wall to access the lungs, pleura, esophagus, diaphragm, or other structures inside the chest. It allows the surgeon to directly examine and treat conditions that require access to the thoracic cavity.
Depending on the child’s condition, thoracotomy may be performed to remove abnormal tissue, repair congenital abnormalities, treat severe chest infections, manage lung lesions, or perform complex reconstructive procedures. It may also be used when minimally invasive surgery is unsuitable or when direct surgical access is required.
The location and size of the incision depend on the area being treated and the operation planned. Thoracotomy is an access technique rather than a single operation, so the specific surgical steps depend on the underlying problem.
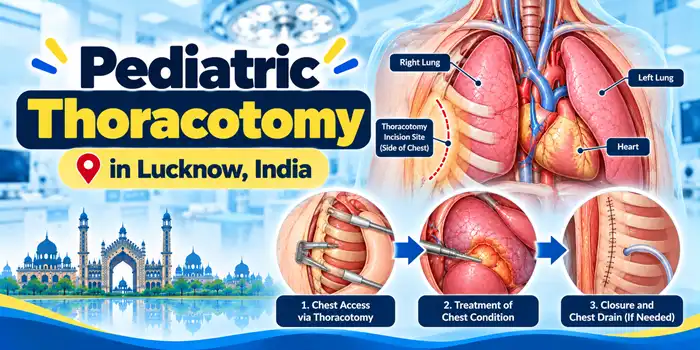
A child may require thoracotomy when a condition inside the chest needs surgical treatment and an open approach is considered appropriate.
Thoracotomy may be used for:
The decision depends on the child’s diagnosis, imaging results, clinical condition, and the surgeon’s assessment.
The primary purpose of thoracotomy is to provide direct access to structures inside the chest so that the required operation can be performed safely.
Depending on the procedure, it may help the surgeon to:
The benefits depend on the operation performed and the child’s underlying condition.
Thoracotomy is generally performed under general anesthesia. The child is positioned according to the planned operation, and the surgical area is prepared.
The surgeon makes an incision in the chest wall to access the required structures. The muscles and tissues are separated carefully, and the ribs may be spread to provide adequate access.
The general steps include:
The specific operation may involve lung resection, drainage, repair, reconstruction, or removal of abnormal tissue.
The type of thoracotomy depends on the location of the condition and the access required.
A posterolateral thoracotomy involves an incision along the side and back of the chest. It provides access to many structures within the chest, including the lungs and esophagus.
It may be used for selected lung operations, esophageal procedures, and complex thoracic surgery.
An anterolateral thoracotomy involves an incision toward the front and side of the chest. It may be used for selected procedures requiring access to the front or side of the thoracic cavity.
The precise incision depends on the operation and the child’s anatomy.
A muscle-sparing thoracotomy is designed to reduce the amount of muscle cutting while still providing adequate access to the chest.
When appropriate, this approach may help preserve muscle function and reduce some aspects of postoperative discomfort. Its suitability depends on the procedure and the access required.
Thoracotomy may be used for selected pediatric lung operations when direct access is needed.
Depending on the condition, the operation may involve:
The amount of lung tissue removed, if any, depends on the diagnosis and the condition of the surrounding lung.
In selected children with advanced empyema, thoracotomy may be required to remove infected material and release a lung trapped by thick fibrous tissue.
During open decortication, the surgeon accesses the pleural space, removes organized infected material, and carefully separates restrictive tissue from the lung where appropriate.
Less invasive approaches, including chest tube drainage and video-assisted thoracoscopic surgery (VATS), may be suitable for other children. Open surgery is considered when the extent or complexity of disease makes it appropriate.
Thoracotomy may provide access to the esophagus for selected pediatric operations.
Depending on the condition, it may be used for procedures involving:
The operation performed through the thoracotomy depends on the child’s anatomy, previous procedures, and the treatment required.
Thoracotomy and thoracoscopy are different ways of accessing the chest.
| Feature | Thoracotomy | Thoracoscopic Surgery |
|---|---|---|
| Access | Open incision in the chest wall | Small incisions with a camera and instruments |
| Visualization | Direct surgical view | Camera-guided view |
| Incision size | Generally larger | Generally smaller |
| Recovery | May involve more chest wall discomfort | May allow faster recovery in selected cases |
| Suitability | Useful for complex procedures or when direct access is required | Suitable for selected conditions and patients |
Neither approach is best for every child. The surgical team chooses the method that provides appropriate access and safety for the planned procedure.
Thoracotomy may be planned for a known condition or performed urgently when a serious chest problem requires immediate surgical treatment.
The timing depends on:
The treating team determines the appropriate timing based on the child’s condition.
Thoracotomy is an established surgical approach, but it is a major procedure and carries risks. The level of risk depends on the operation being performed, the child’s age, underlying condition, and respiratory health.
The team evaluates the child before surgery and plans anesthesia, pain relief, respiratory support, and postoperative monitoring as required.
Some children may need care in a pediatric intensive care unit, particularly after complex surgery or when respiratory support is required.
Potential benefits include:
The benefits depend on the specific operation and the condition being treated.
Possible complications include:
The surgical team discusses the risks associated with the specific operation rather than thoracotomy alone.
Recovery depends on the operation performed, the child’s health, and whether complications occur.
After surgery, the child is monitored for pain, breathing, oxygen levels, and chest drainage when a drain has been placed.
Recovery may include:
Children who undergo complex surgery or have significant lung disease may need a longer hospital stay.
Parents should follow the surgeon’s instructions carefully after discharge.
Important measures include:
Severe breathlessness, bluish lips, or sudden deterioration requires emergency medical attention.
Follow-up appointments help the surgical team assess healing and recovery.
The team may review:
The follow-up schedule depends on the procedure performed and the child’s progress.
The timing depends on the extent of surgery and the child’s recovery.
Light activities may be resumed gradually when the surgical team considers it safe. Strenuous activity, heavy lifting, and contact sports may need to be avoided until adequate healing has occurred.
Children who undergo extensive lung or esophageal surgery may need an individualized return-to-activity plan.
Many children recover well after thoracic surgery, but long-term outcomes depend on the underlying condition and the procedure performed.
Some children may need continued respiratory follow-up, nutritional support, or monitoring of chest wall movement and exercise tolerance.
Regular follow-up helps identify persistent symptoms and ensures that the child receives any additional care needed.
The cost varies according to the operation, the child’s medical condition, and the hospital facilities required.
Factors that may affect the total cost include:
Parents should request an individualized estimate from the hospital after the surgical plan has been established.
Parents should understand that thoracotomy is the surgical access method; the actual operation depends on the condition being treated.
Useful questions to discuss with the surgeon include:
Pediatric thoracotomy is an operation in which the surgeon makes an incision in the chest wall to access structures inside the chest and perform the required procedure.
It may be used for selected lung conditions, severe empyema, esophageal abnormalities, chest masses, and other conditions requiring open access to the thoracic cavity.
No. Thoracotomy describes the surgical approach used to access the chest. The operation performed may involve the lungs, esophagus, pleura, or other thoracic structures.
Sometimes. Thoracoscopic surgery uses small incisions and a camera and may be suitable for selected conditions. Open surgery may be preferred when more direct access is needed.
A chest tube may be placed to drain air or fluid from the chest after certain operations. Whether it is required depends on the procedure and the surgeon’s assessment.
Recovery varies according to the underlying condition, the operation performed, and the child’s health. The treating team provides an individualized recovery plan.
Yes. Thoracotomy is a major surgical approach, and the risks and recovery depend on the specific procedure performed through the incision.
Dr. Muni Varma offers Pediatric Thoracotomy Surgery for Children in Lucknow, India. With more than 10 years of experience, he uses a careful and child-focused approach to provide appropriate evaluation, surgical planning, and follow-up care. He helps parents understand the surgical approach, available treatment options, and expected recovery for children requiring thoracic surgery.
