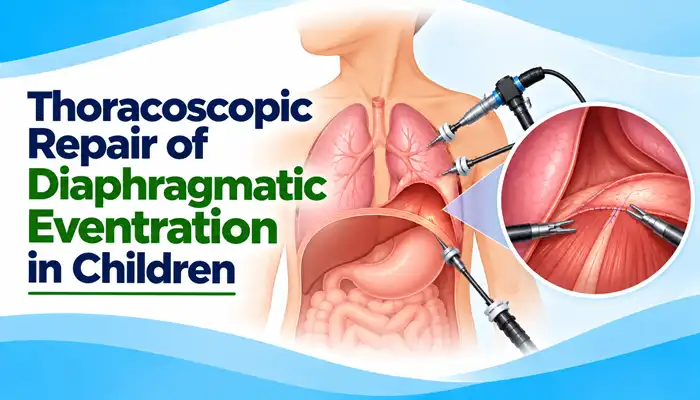
Thoracoscopic repair of diaphragmatic eventration is a minimally invasive surgical procedure used to correct an abnormally elevated portion of the diaphragm in children. During the operation, the surgeon uses a small camera and specialised instruments inserted through small incisions in the chest to tighten and strengthen the affected diaphragm.
The diaphragm is a dome-shaped muscle that separates the chest from the abdomen and plays an essential role in breathing. In diaphragmatic eventration, part of the diaphragm is unusually thin, weak, or elevated because of abnormal muscle development or impaired nerve function. This can allow the abdominal organs to push upward and reduce the space available for the lungs to expand.
Thoracoscopic repair of diaphragmatic eventration in children is generally performed through a technique called diaphragmatic plication. The surgeon folds and stitches the elevated portion of the diaphragm to bring it into a lower, more functional position.
The procedure may be recommended for children with significant breathing difficulties, recurrent respiratory infections, or other symptoms associated with diaphragmatic eventration. The decision depends on the severity of symptoms, imaging findings, the child’s overall health, and the expected benefits of surgery.
Not every child with diaphragmatic eventration requires surgery. Children with mild abnormalities and no significant symptoms may be monitored by their treating team.
Surgical repair may be considered when diaphragmatic eventration affects breathing, feeding, or overall health.
Common indications include:
The decision to operate is individualised. The surgeon evaluates whether the symptoms are genuinely related to diaphragmatic eventration and whether correcting the diaphragm is likely to improve the child’s condition.
The primary goal of thoracoscopic repair is to reposition the elevated diaphragm so that the lungs have more room to expand during breathing.
The procedure aims to:
The extent of improvement depends on the severity of the original condition and whether other lung, heart, nerve, or respiratory problems are present. Surgery does not guarantee that all breathing difficulties or recurrent infections will resolve.
Thoracoscopic diaphragmatic plication is performed in an operating theatre under general anaesthesia. The surgeon uses a camera and specialised instruments to tighten the elevated diaphragm through small chest incisions.
The doctor reviews the child’s symptoms, medical history, previous respiratory problems, and imaging results. The team assesses whether diaphragmatic eventration is responsible for the child’s symptoms and whether a minimally invasive procedure is appropriate.
The child receives general anaesthesia and is monitored throughout the operation. The anaesthesia team pays particular attention to breathing, oxygen levels, circulation, and the child’s overall stability.
The child is positioned to provide access to the affected side of the chest. The surgeon makes several small incisions through which the thoracoscope and surgical instruments are introduced.
The camera displays the diaphragm and surrounding structures on a monitor, allowing the surgeon to work without making a large chest incision.
The surgeon identifies the elevated portion of the diaphragm and assesses its appearance and the available space within the chest. The precise technique depends on the location and extent of the eventration.
The surgeon folds the redundant or elevated portion of the diaphragm and places sutures to tighten it. This reduces the abnormal elevation and creates a flatter, more functional position.
The aim is to improve the mechanical relationship between the diaphragm, lungs, and abdominal organs.
The surgeon checks the plication and surrounding structures before completing the procedure. If the anatomy, available working space, or the child’s condition makes thoracoscopic surgery unsafe, conversion to an open operation may be necessary.
The instruments are removed, and the small incisions are closed. A chest drain may be placed when clinically indicated, but it is not required in every case.
The child is then monitored in a recovery area or intensive care unit, depending on age, respiratory status, and the complexity of the operation.
The surgical approach depends on the location and severity of the eventration, the child’s condition, and the treating surgeon’s assessment.
This minimally invasive procedure uses a camera and instruments inserted through small chest incisions. The elevated diaphragm is folded and secured with sutures to reduce its height.
An open thoracic approach involves an incision in the chest to access the diaphragm directly. It may be recommended when thoracoscopic repair is unsuitable or when the anatomy requires a more direct approach.
In selected cases, plication may be performed using a laparoscopic approach through small abdominal incisions. The appropriate route depends on the underlying condition, the location of the abnormality, and the surgeon’s expertise.
Different suturing techniques may be used to tighten the diaphragm, including interrupted sutures, continuous sutures, and selected folding or pleating techniques. No single technique is suitable for every child.
The surgeon chooses the approach that provides an appropriate repair while minimising the risk of injury and recurrence. Published pediatric studies support the feasibility of thoracoscopic plication in selected children, although individual outcomes vary.
Preoperative investigations help confirm the diagnosis, assess the effect on breathing, and determine the safest surgical approach.
These may include:
The exact tests depend on the child’s age, symptoms, medical history, and the findings from the initial assessment.
For children who are suitable candidates, thoracoscopic repair may offer several potential advantages over an open chest operation.
These include:
The extent of benefit varies. A minimally invasive approach is not automatically the safest option for every child, and the surgeon may recommend open repair when it is more appropriate.
Thoracoscopic diaphragmatic plication is an established option for selected children with symptomatic diaphragmatic eventration. However, as with any operation, it carries risks.
Possible complications include:
The likelihood of complications depends on the child’s medical condition, the severity of the eventration, associated abnormalities, and the surgical approach.
Parents should discuss the expected benefits, risks, alternatives, and possibility of recurrence with the treating team before surgery.
Recovery varies according to the child’s age, respiratory condition, associated medical problems, and the complexity of the repair.
The child is monitored as they recover from anaesthesia. The medical team checks breathing, oxygen levels, circulation, pain, and the condition of the surgical incisions.
Some children breathe independently after surgery, while others may need temporary oxygen or ventilatory support. Children who had significant respiratory problems before the operation may require longer monitoring.
Feeding is restarted according to the child’s condition and medical team’s advice. Infants who require respiratory support or have additional health problems may need a gradual feeding plan.
The length of the hospital stay depends on respiratory recovery, pain control, feeding, and whether complications occur. Children with additional medical conditions may require a longer admission.
Before discharge, parents receive instructions about wound care, medicines, activity, and follow-up appointments. The surgeon explains when the child can return to routine activities.
Appropriate aftercare supports healing and helps identify complications early.
Parents should:
Seek medical advice if the child develops fever, worsening pain, persistent vomiting, poor feeding, or new or worsening breathing difficulties. Severe breathing difficulty or sudden deterioration requires emergency medical assessment.
Follow-up is important to assess whether the diaphragm remains in an appropriate position and whether the child’s breathing improves.
The treating team may recommend:
Some children improve substantially after repair, while others may continue to experience symptoms because of associated lung disease, nerve dysfunction, or other medical conditions. Recurrence or incomplete correction may occasionally require further evaluation or treatment.
The follow-up schedule should be tailored to the child’s condition and surgical findings.
Although both conditions affect the diaphragm, they are different.
Diaphragmatic eventration occurs when part of the diaphragm is abnormally elevated because it is thin, weak, or poorly functioning. The diaphragm remains intact, and treatment may involve plication to lower and tighten it.
Congenital diaphragmatic hernia (CDH) involves an actual opening in the diaphragm through which abdominal organs can move into the chest. Treatment generally involves returning the displaced organs to the abdomen and repairing the opening.
The distinction matters because the surgical techniques, treatment planning, and associated risks are different. The diagnosis should be confirmed before selecting a procedure.
The cost of thoracoscopic diaphragmatic eventration repair varies depending on the hospital, the child’s age and condition, the complexity of the operation, and the length of hospitalisation.
Factors that may influence the overall cost include:
Children who have significant respiratory problems or other medical conditions may need additional care. Parents should request an individual estimate after clinical assessment so that the expected expenses can be explained clearly.
Before proceeding with thoracoscopic repair, parents should understand why the operation has been recommended and what improvements can reasonably be expected.
Important points to discuss include:
Parents should share information about the child’s medical conditions, medicines, allergies, previous operations, and respiratory history with the treating team.
It is a minimally invasive procedure used to tighten and lower an abnormally elevated portion of the diaphragm. The surgeon uses a camera and specialised instruments inserted through small incisions in the chest.
No. Children with mild eventration and no significant symptoms may be monitored. Surgery is considered when the condition causes meaningful respiratory symptoms or other complications.
Diaphragmatic plication is a surgical technique in which the elevated diaphragm is folded and stitched to reduce its height. It aims to improve the diaphragm’s position and allow better lung expansion.
Thoracoscopic repair offers smaller incisions and may reduce chest wall disruption. However, the safest approach depends on the child’s anatomy, respiratory condition, and the surgeon’s assessment. Open surgery may be preferable in some cases.
Surgery may be considered in infants, young children, or older children when symptoms and clinical findings justify intervention. The timing depends on the severity of symptoms, the child’s condition, and the expected benefits of repair.
Recovery varies. Some children recover relatively quickly, while those with respiratory difficulties or associated medical conditions may need longer hospitalisation and monitoring. The treating team provides guidance based on the child’s progress.
Recurrence or incomplete correction can occur. Follow-up helps assess diaphragm position and identify persistent or returning symptoms that may need further evaluation.
The procedure may improve breathing when the elevated diaphragm is an important cause of the child’s symptoms. The degree of improvement depends on the severity of the condition and the presence of other lung, nerve, or heart problems.
No large chest incision is usually required. The procedure uses small incisions, so visible scarring is generally limited, although the final appearance varies with healing and individual skin characteristics.
Parents should seek medical advice if the child develops fever, worsening pain, poor feeding, persistent vomiting, or new or worsening breathing difficulties. Severe breathing difficulty requires emergency assessment.
Dr. Muni Varma offers Thoracoscopic Repair of Diaphragmatic Eventration in Children in Lucknow, India. With more than 10 years of experience, he uses a careful and child-focused approach to provide appropriate evaluation, surgical planning, and follow-up care. He helps parents understand the surgical approach, available treatment options, and expected recovery for children requiring diaphragmatic eventration repair.
